Saturday, December 25, 2010

Meniere's disease Second edition

History:


In late 19th century Prosper Meniere described a condition characterized by ear block, tinnitus, and vertigo. He even correctly identified the site of lesion to be labyrinth. It wont be a understatement to say that precious little has been added to the knowledge and understanding of the disorder since then. Prosper Meniere infact lived far ahead of his time. He was born in 1799 in France. In 1848 he began to translate the text book on hearing loss authored by Kramer. The book was written in German. This kindled his interest in otology.
In his classical seminal reports he goes on to describe a series of patients who presented with neural deafness, with hearing loss greater for low frequencies. Deafness was commonly unilateral in these patients. These patients usually  present with tinnitus, vertigo, nausea and vomiting. He reported that these patients had a normal ear drum. He also reported that these symptoms were completely reversible.

Download the e book from here:


Thursday, December 23, 2010

Open conservative partial laryngectomy

Introduction:
Organ preservation is becoming common these days. This applies
to larynx also. Laryngeal malignancies if identified early can be
effectively managed by conservative resection procedures of
larynx.
Advantages of organ preservation:
1. The patient need not live with the stigma of permanent
tracheostomy
2. Speech is preserved to the maximum extent
3. There is effective separation of air and food channels
4. Post operative recovery is very fast
5. Option of salvage total laryngectomy is still an option if the
conservative procedure fails

Read the complete e book from here

Tuesday, December 14, 2010

Vertical partial laryngectomy

Introduction:


Vertical partial Laryngectomy is a conservative laryngeal surgical procedure which involves removal of one half of the larynx while the other half is preserved. The dead space created after removal of one half of the larynx is closed using various flaps. This surgery was first proposed by Solis – Colen in 1869 to manage early malignant lesions involving vocal folds.


Indications:


1. Malignant tumors involving a single vocal cord early T1, T2 and select T3 lesions


2. Anterior commissure of the vocal cord should be free of the lesion


This surgery is not suitable for patients with growth vocal cord involving the anterior commissure and the opposite cord.


Advantages:


1. This is a conservative procedure where in patient is able to speak without the aid of prosthesis


2. Patient need not have a permanent tracheostome


3. Patient does not have any swallowing problems


You can view the video clipping of the surgery below:
 

Monday, December 06, 2010

Tumor Biology pertaining to laryngeal malignancy

Introduction:


Recent advances in tumor biology and genetics have increased our understanding of the basic mechanisms involved in the development of laryngeal malignancy and in predicting its clinical course. The following genes / enzymes may be of use in diagnosis & in predicting the prognosis of various malignant lesions involving the larynx.


Telomerase:


A brief introduction to this enzyme is a must. A telomere is a repeating DNA sequence at the end of the chromosome. They can reach a length of 15,000 base pairs. These telomeres function by preventing the chromosome from losing base pair sequence at their ends. They also prevent chromosomes from fusing with each other. Each time a cell undergoes division some amount of telomere is lost. When the telomere becomes too short the chromosome reaches a critical length and can no longer multiply. The cell which contains this critical length chromosome is considered to be too old and undergoes cell death (apoptosis). The length of the telomere is controlled by two mechanisms:


Erosion – Occurs each time a cell divides


Addition – This is determined by the activity of telomerase


Telomerase is an enzyme made of protein and RNA subunits. It elongates the chromosomes by adding TTAGGG sequences to the end of the existing chromosomes. This enzyme is found in abundance in fetal cells, germ cells and tumor cells. If this enzyme telomerase is activated in a cell it continues to grow and divide and is known as the “Immortal cell”.


This enzyme has been linked to carcinogenesis of larynx. The presence of this enzyme in the laryngeal cancer specimen serves as a marker in diagnosing persistent malignancy after irradiation. It is very helpful in picking up radio resistant cases / recurrent cases following irradiation.


PH-20:


This is a hyaluronidase usually expressed by malignant tissues. It is usually found to be elevated in metastatic lesions and hence can be used as a valuable tumor marker in identifying early nodal metastasis.


Herpes simplex virus DNA:


Polymerase chain reaction can be used to identify Herpes simplex virus DNA. This is found to be positive in nearly 75% of patients with laryngeal malignancies. This is due to the fact that this virus protein is a proved carcinogen.


Mutations involving gene p53:


Mutations involving gene p53 correlates with the clinical outcome of patients with laryngeal cancer.


Retinoblastoma protein:


Negative expression of this protein has been associated with higher likelihood of lymph node metastasis with significantly lower 5 years survival rates.


Cyclin D1:


This has been identified by immuohistochemical staining of paraffin embedded specimen. Low levels of cyclin D1 have been associated with radio resistance.

Sunday, November 28, 2010

Haller cell

Synonyms: These are also known as Infra orbital recess cells.

Introduction:
These are pneumatized ethmoid air cells that project along the medial roof of the maxillary sinus and the most inferior portion of the lamina papyracea.
This air cell lies below the ethmoid bulla and lateral to the uncinate process.

Commonly these cells arise from anterior ethmoid air cells and are closely related to the infundibulum. Rarely these cells can arise from posterior
ethmoidal cells in which case it does not compromise the infundibulum.

Infections involving these cells can compromise and narrow the infundibulum causing obstruction to the drainage of maxillary sinus ostium.  It has been suggested that infections involving these cells could be a factor in recurrent maxillary sinusitis.


Thursday, November 25, 2010

Monday, November 22, 2010

CSF rhinorrhoea repair using bicoronal approach

Clinical details:

30 years old male patient came with c/o watery discharge from left nasal cavity - 3 years duration
H/O Road traffic accident 3 years back following which watery discharge started.
H/O meningitis 2 years back for which he was treated.
H/O Head ache on and off ++.

On examination:

Watery discharge was seen flowing out of left nasal cavity. It was more pronounced when the patient bent down.

Imaging:

CT paranasal sinus showed fracture involving the posterior table of frontal sinus with evidence of pneumatocele in the left
frontal lobe.


Management:

Since the fracture was present laterally in the posterior table of frontal sinus external approach was preferred.
Bicoronal approach was used to expose the anterior table of frontal sinus.
The incision begins in the preauricular crease at the level of tragus and traverses the scalp 3-4 cms behind the hair line.
The incision is carried down through the galea to the loose alveolar plane above the calvarial periosteum and the deep temporal
fascia and the flap is elevated anteriorly until approximately 2cms above the supra orbital rims. At this point the periosteum is
incised and the dissection is continued in the subperiosteal plane. The supraorbital neurovascular bundles are protected.
Laterally the dissection continues in the subgaleal plane up to 1-2 cms above the zygomatic arch. The deep temporal fascia
is incised at this point and the dissection continues deep to the temporal pad of fat over the temporalis muscle and the investing
fascia. The deep temporal artery perforators should be protected if not this could lead to a hallowing in the temoporal area due
to wasting of temporalis muscle.
The anterior table of frontal sinus is exposed. A window is created over the anterior table of frontal sinus using a fissure burr.
The interior of frontal sinus was visualized and the leak was identified over the posterior table of left frontal sinus which was
sealed using tissue glue and abdominal fat.


window.JPG


Friday, November 19, 2010

Interesting case of fibroma sphenoid sinus

Clinical details:

18 years old boy came with c/o blocking sensation both nasal cavity - 1 year duration
Decreased sensation of smell - 6 months duration
He gave h/o repeated attacks of upper respiratory infection
He gave no h/o bleeding from nose
No h/o head ache

On examination:

Anterior rhinoscopy:
A pale mass could be seen occupying the posterior portion of right nasal cavity.
Post nasal examination:
The same mass could be seen occupying the nasopharynx occluding both choana.

CT scan nose and paranasal sinuses plain / contrast were taken.

It showed non enhancing mass arising from sphenoid sinus entering the post nasal space and the posterior portion of right nasal cavity.


Management:

This patient was taken up for endoscopic sinus surgery and the mass was removed completely in toto.
Histopathology report - fibroma
Fibroma involving sphenoid sinus and post nasal space are commonly vascular (angiofibroma). In this case the fibrous elements
predominated and hence the mass was not enhancing in contrast CT. There was no abnormal bleeding during surgery.


Saturday, November 06, 2010

The Tamilnadu Dr MGR Medical University MS (ENT) Basic sciences march 2009 question paper with solution

In my continuing effort to help out post graduate students of otolaryngology I have uploaded the MS (ENT) Basic sciences question paper with solutions of Tamilnadu Dr MGR Medical university.

Basic sciences post graduate question papers have always been dicey.  Unless you prepare diligently for the same you may encounter pit falls.  The whole question paper has been broken down into sub topics i.e. anatomy, physiology, pathology and biochemistry.  Since each of these sections will be evaluated by different examiners belonging to basic sciences department you need to concentrate equally on all these sections.

You can access the question paper with solutions from here.

Friday, October 29, 2010

Lingual thyroid and its management

Clinical details:

6 years old female patient came with complaints of:
1. Difficulty in swallowing - 6 months
2. Occasional episodes of bleeding from mouth - 2 months

On examination:

Oral cavity: Pinkish globular mass could be seen in the posterior 1/3 of tongue. The mass was firm on palpation. The posterior border of the mass was not visible on oral examination.
Both tonsils were found to be enlarged grade III.


Radiology:

X ray soft tissue neck lateral view:


X ray soft tissue neck lateral view showing mass in the suprahyoid region occupying posterior 1/3 of tongue.
Axial CT scan of neck showing mass involving the posterior 1/3 of tongue.


Contrast CT axial view showing absent thyroid gland in the neck
Ultrasound neck: Absent thyroid gland in the neck

Thyroid profile:

Pt was euthyroid with normal serum T3 T4 and TSH levels

Management:

Patient was taken up for surgery.
supra hyoid midline approach was preferred.
Skin crease incision is made just below the hyoid bone in the neck.
Skin flap elevated in the subplatysmal plane. Hyoid bone was exposed.
Supra hyoid muscles were resected from the superior border of hyoid bone
Mylohyoid muscle fibers are resected and retracted. Lingual thyroid mass removed in toto and the wound closed in layers.

Discussion:

Lingual thyroid is a rare embryonic aberration with an incidence rate of 1 in 100,000 individuals.
This condition is invariably due to failure of descent of thyroid gland. Parathyroid glands in these patients will
be found in the neck in their normal positions because of their separate origin embryologically.
Symptoms are invariably caused due to the mass effect of the lesion. It has also been pointed out that these
ectopic thyroid gland may not be in a position to cater to the increasing demands of thyroxine during menarche / pregnancy and
may undergo enlargement causing increasing symptoms. Incidence of malignancy is also more in ectopic thyroid glands hence
it is always better to resect the gland and place the patient under supplemental thyroid hormones.
Surgical approaches:
1. Removal via the oral cavity: This is the commonly practiced approach. This approach has the advantage of avoiding neck incisions.
The mouth of the patient is kept open by using Boyle's Davis mouth gag. Using either diathermy / laser / cobalator the dissection is
started from the anterior border of the mass and it is removed totally by encircling incision. Bleeders if any can be cauterized using
a bipolar cautery. This approach is advisable if the posterior border of the lesion is visible on opening the mouth.
2. Suprahyoid midline approach: This is another commonly used approach which has been described already. This lesion is useful
in patients with large lingual thyroid mass.
3. Lateral pharyngotomy approach: This approach is useful in removing big mass with a predominant vascular supply from the lingual
artery. This approach will also facilitate repositioning of ectopic thyroid mass in the neck.
4. Midline mandible and tongue splitting approach: Useful in adults with a huge lingual thyroid mass. The mandible is slit in the midline
by performing a midline osteotomy. The tongue is slit right in the middle till the foramen cecum portion is reached. The lingual
thyroid mass is removed in an encircling manner.



Saturday, October 23, 2010

Fibrous dysplasia posterior ethmoid with blindness

Complaints:

48 years old male patient came with complaints of loss of vision left eye - 6 months duration.
Persistent left nasal block - 4 years
Discharge from left nose - 4 years
Head ache more on the left side - 5 years (Deep boring in nature)

Past history:

No history of epistaxis
No history of loss of smell

On examination:

Anterior rhinoscopy was unremarkable.
Post nasal examination normal.
Vision was absent in the left eye.

Imaging:


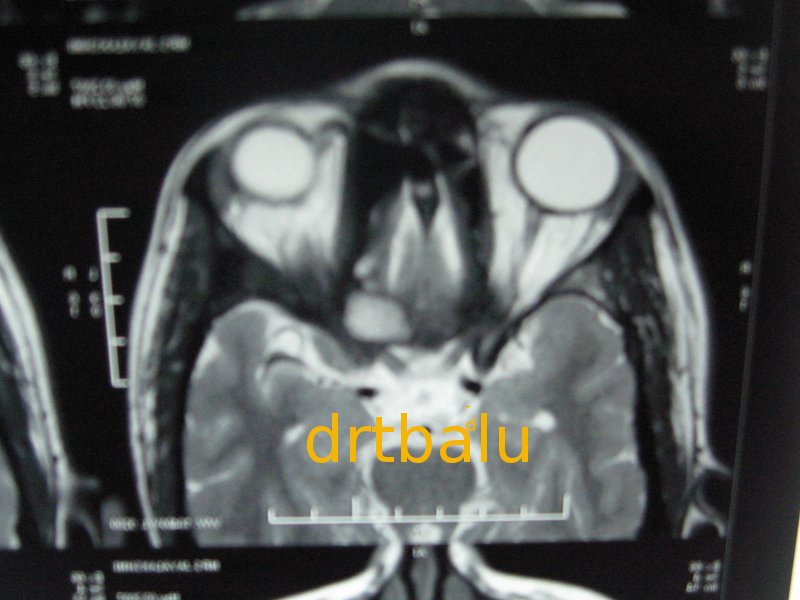
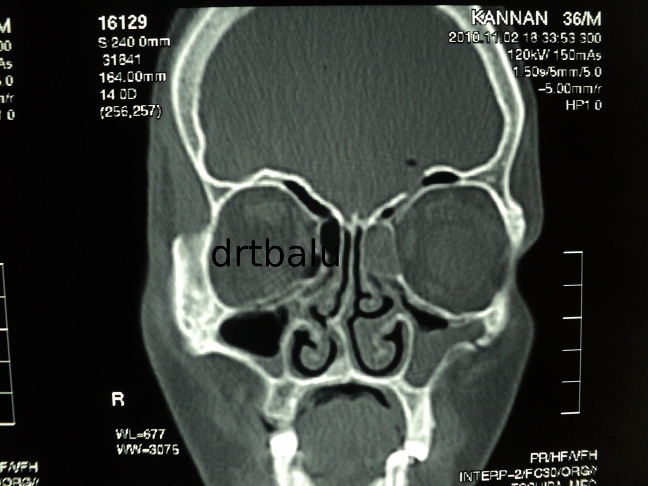
CT scan plain axial cut paranasal sinuses show heterodense mass arising from left posterior ethmoid air cells extending up to the anterior face of sphenoid. The mass could be seen compressing the left optic nerve. Diagnosis (Fibrous dysplasia)


MRI showing mass arising from posterior ethmoidal air cells on the left side compressing the left optic nerve.


Management:
This patient was taken up for endoscopic surgery. The mass from the left side of the nasal cavity was progressively drilled out under endoscopic vision.


Discussion:

The term fibrous dysplasia was first introduced by Litchtenstein in 1938. Usually fibrous dysplasias affect children commonly
in their teens (during the growth phase).
In any fibrous dysplasia involving the nasal cavity and paranasal sinuses the clinical presentation
is initially related to sinus obstruction, visual disturbance, facial asymmetry and nasal blockage.
In fibrous dysplasia the normal woven bone is replaced by isomorphous fibrous tissue and poorly
formed woven bone.

Classification:

Fibrous dysplasias have been classified into:
Monostotic - Involves single bone
Polyostotic - Involves multiple bones
Albright's syndrome - Endocrine hyperfunction, Unilateral Café-au-lait spots, and polyostotic fibrous dysplasia
Among these types the monostotic fibrous dysplasia is more common accounting for 70% of all fibrous dysplasias.
Rarely fibrous dysplasia may become more aggressive and dedifferentiate causing (desmoplastic fibroma). Sometimes the tissue may undergo sarcomatous transformation.
Excision of these mases makes sense because of their propensity to undergo malignant transformation.
Risk factors for malignant transformation include:
1. Polyostotic form
2. Post radiation sequelae
3. Facial bone involvement
4. Albright's syndrome


Fibrous dysplasia posterior ethmoid with blindness

This is an interesting case report of a patient with fibrous dysplasia of posterior ethmoid with blindness.

Complaints:

48 years old male patient came with complaints of loss of vision left eye - 6 months duration.
Persistent left nasal block - 4 years
Discharge from left nose - 4 years
Head ache more on the left side - 5 years (Deep boring in nature)

Past history:

No history of epistaxis
No history of loss of smell

On examination:

Anterior rhinoscopy was unremarkable.
Post nasal examination normal.
Vision was absent in the left eye.

Imaging:


<>


CT scan plain axial cut paranasal sinuses show heterodense mass arising from left posterior ethmoid air cells extending up to the anterior face of sphenoid. The mass could be seen compressing the left optic nerve. Diagnosis (Fibrous dysplasia).


MRI showing mass arising from posterior ethmoidal air cells on the left side compressing the left optic nerve.

Management:
This patient was taken up for endoscopic surgery. The mass from the left side of the nasal cavitywas progressively drilled out under endoscopic vision.


Discussion:

The term fibrous dysplasia was first introduced by Litchtenstein in 1938. Usually fibrous dysplasias affect children commonly
in their teens (during the growth phase).
In any fibrous dysplasia involving the nasal cavity and paranasal sinuses the clinical presentation
is initially related to sinus obstruction, visual disturbance, facial asymmetry and nasal blockage.
In fibrous dysplasia the normal woven bone is replaced by isomorphous fibrous tissue and poorly
formed woven bone.

Classification:

Fibrous dysplasias have been classified into:
Monostotic - Involves single bone
Polyostotic - Involves multiple bones
Albright's syndrome - Endocrine hyperfunction, Unilateral Café-au-lait spots, and polyostotic fibrous dysplasia
Among these types the monostotic fibrous dysplasia is more common accounting for 70% of all fibrous dysplasias.
Rarely fibrous dysplasia may become more aggressive and dedifferentiate causing (desmoplastic fibroma). Sometimes the tissue may undergo sarcomatous transformation.
Excision of these mases makes sense because of their propensity to undergo malignant transformation.
Risk factors for malignant transformation include:
1. Polyostotic form
2. Post radiation sequelae
3. Facial bone involvement
4. Albright's syndrome

Friday, October 22, 2010

The Tamilnadu Dr MGR Medical University MBBS Prefinal Otolaryngology March 2010 question paper with solution

The Tamilnadu Dr MGR Medical University MBBS Prefinal Otolaryngology March 2010 question paper with solution has been uploaded.

Get it from here.

Thursday, October 14, 2010

Interesting case report of invasive mucor mycosis causing palatal destruction

Clinical details:
38 years old female
Diabetic on poor glycemic control
Complaints:

Ulcerative lesion of right side of hard palate - 2 years
Devitalization of upper premolars - 6 months
On examination:

Nasal cavity - Whitish mass seen inside the right nasal cavity. The mass was insensitive to touch and cheesy.
Floor of right nasal cavity found to be eroded.

Oral cavity - Slough covered lesion seen in the right side of hard palate. On probing there was no bone palpable
through the slough.


Investigations:
Biopsy from the lesion was reported as mucormycosis.
These fungi can be seen as large number of aseptate ribbon like hyphae with right / obtuse angle branching in necrotic tissue.

Imaging:


Ct scan showing heterodense mass occupying the right maxillary sinus with destruction of its medial wall.
The mass could be seen extending to the right nasal cavity with destruction of the floor of right nasal cavity.

Discussion:

Synonyms include - zygomycosis / phycomycosis
Two main types of mucor mycosis infections occur in humans. They are superficial and visceral.
Superficial mucormycosis involves external ear, fingers and skin commonly.
The visceral form could be Gastrointestinal, rhinocerebral, pulmonary or disseminated.
Visceral forms of mucor infections are common in diabetics and immune compromised individuals.
Among these visceral types the rhinocerebral type is the most common. This is due to the fact that the
nasal mucosa is normally colonized by mucor. Rhinocerebral mucor mycosis can be subclassified into two types.
They include:
Type I - Rhino orbito cerebral. This form is highly fatal
Type II - Rhinomaxillary form. This form is not fatal. This case belongs to type II category.
Mucor infections has a strong prediliction to involve blood vessels, nerves and lymphatics. Invasion of arteries causes
avascular necrosis of the infected area.
Mucor is known to thrive in acidic and glucose rich medium, which is common in a diabetic. Hyperglycemia also impairs
neutrophil chemotaxis thereby reducing immunity.
In addition increased availability of micronutrients like iron in diabetics increase the pathogenecity of the organism.

Management:

Is by wound debridment.
Control of diabetes.
Administration of amphoteracin B.


Tuesday, October 05, 2010

Tamilnadu Dr MGR Medical Univeristy MBBS Prefinal otolaryngology september 2010 question paper with solution has been upped

The Tamilnadu Dr MGR Medical University Prefinal MBBS otolaryngology September 2010 question paper with solution has been released. Access it from here.

Monday, October 04, 2010

drtbalu's otolaryngology resources: Laryngomalacia

drtbalu's otolaryngology resources: Laryngomalacia: "Introduction: The term Malakia in Greek means softening. The term indicates softening of larynx. This is a disease of infants and children..."

Laryngomalacia

Introduction:

The term Malakia in Greek means softening. The term indicates softening of larynx.
This is a disease of infants and children. This disease is characterised by the presence of stridor which is caused due to excessive redundancy of supraglottic tissues which gets sucked into the glottis due to the negative pressure caused during inspiration. The stridor in these patients are inspiratory in nature.

Age of onset:
This condition gets manifested within first two weeks after birth and usually resolves when the child reaches the age of 2.

Pathophysiology:

1.Excessive redundancy of supraglottic soft tissues
2.Immaturity of neuromuscular system
3.Immaturity of cartilages of larynx
4.GERD
5.Submucosal gland hyperplasia

Possible mechanisms causing stridor in these patients include:

1.Indrawing of cuneiform cartilages on inspiration
2.Omega shaped epiglottis of infants curls upon itself
3.The arytenoids collapse inwards
4.The epiglottis gets displaced against the posterior pharyngeal wall
5.Short aryepiglottic folds
6.Overtly acute angle of epiglottis at the laryngeal inlet

Get the full article from here.

Monday, September 27, 2010

Sialendoscopy

Introduction:

Common disorders of salivary glands involve obstruction involving their ductal system. Salivary gland calculi comprises the most common cause of enlargement of salivary glands. Obstructions could be caused by the presence of calculi, strictures of the duct etc. Sialoendoscopy is the most preferred mode of treating obstructions involving major salivary glands. Major advantage of this procedure is that it can be performed under local anesthesia as an office procedure.

History:

It was Konigsberger and his colleagues first used sialoendoscopy and lithotripsy to treat salivary gland calculi in 1990. During the year 1991 Gundlach and colleagues published their experience of doing sialoendoscopic procedures. Katz in 1991 used a 0.8 mm flexible endoscope to diagnose sialolithiasis and to remove them from major salivary glands. It was Kongisberger and colleagues who successfully used a flexible mini endoscope and intracorporeal lithotriptor to fragment major salivary gland calculi, thus opening up new vistas.
In 1994 Arzoz and his colleagues first introduced a 2.1 mm rigid endoscope which had a 1mm working channel as sialendoscope. This was indeed a mini urethroscope. They also used a Pneumoballistic lithotriptor along with this endoscope to hit the calculus and break it. This work was followed by Nahlieli who published his three years experience with rigid sialendoscope in the year 2000.


Read the full e book from here

Tuesday, September 14, 2010

Pseudocyst of Pinna

This condition involves the Pinna and can frequently recur even after successful treatment. It goes by various names i.e. intercartilagenous cyst, endochondral Pseudocyst and idiopathic cystic chondromalacia. This condition was first described by Engel in 1966.

Clinical features:

1.Presents as painless, spontaneous dome shaped cystic swelling on the anterior surface of auricle.
2.This condition is predominantly seen in adult males
3.It is uncommon before 20 and after 60 years of age.
4.Majority of these cysts are found in the scaphoid and triangular fossae of the pinna
5.Majority of these cysts have been reported in Chinese. Chinese have attributed this problem due to the firm pillow they use to sleep. Studies have not demonstrated any racial differences.
6.Right ear is more commonly affected than the left. This has been attributed to the habit of majority of individuals to sleep on their right side.

Read the full article from here

Monday, September 13, 2010

Congenital Epulis

Introduction:
“Epulis” is a Greek term meaning Gums. This term is used to denote a wide variety of lesions involving the gums regardless of their pathology.
This is a rare congenital growth affecting the gingival mucosa of neonates. It is also known as Neumann’s tumor. It is truly a benign condition affecting predominantly female infants. It may even be multiple. This tumor was first described in 1871 by Neumann and hence the name.

These tumors are commonly present at birth arising from the gingival mucosa of maxilla / mandible. These infants may have feeding and breathing difficulties because of the mass effect. Ultrasound studies have shown that this tumor can arise as early as 26th week of gestation.

Get the whole article from here.